Infertility Treatment

Infertility Treatment
Science that advances.
Care that follows every step
of your treatment.
Here, you don't have to explain more than you've already felt. We investigate your causes with technical rigor, explain the possibilities with honesty, and stay with you until the path becomes clear.
Dealing with infertility takes more than clinical treatment: it takes time and attention to every decision. We bring together scientific knowledge and a team available to explain, together with you, every step - from the first contact to defining the protocol.
Low-Complexit Tratment

Coito Programado (CP)
Indicated for cases of unexplained infertility or low-complexity cases. We monitor the cycle with ultrasound exams and, when necessary, use medication to stimulate ovulation.
Based on the most fertile day, we advise the recommended time for intercourse.

Intrauterine Insemination (IUI)
After using medication, usually oral, we monitor ovulatory response with ultrasounds to identify the most fertile day.
On that day, we collect the sperm - from a partner or donor -, prepare it in the lab, and insert it directly into the uterus.
High-Complexity Treatment
In Vitro Fertilization (IVF)
We begin treatment by stimulating the ovaries with medication, usually injectable, and we monitor this response with ultrasound throughout the cycle.
When the follicles reach the ideal size, we collect the eggs in a procedure performed in our surgical center and fertilize them in the lab with the partner's or a donor's sperm. If viable embryos form, we perform the transfer to the uterus.
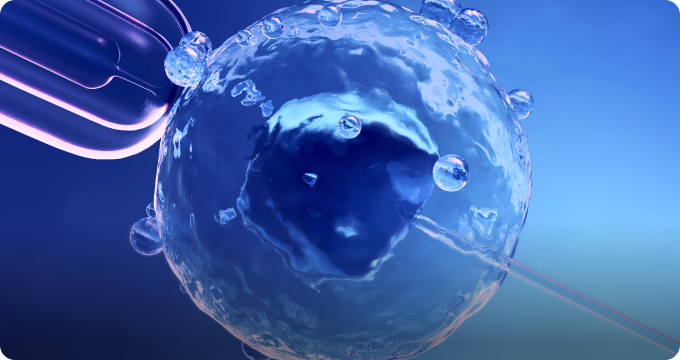
Intracytoplasmic Sperm Injection (ICSI)
Indicated when there is a reduced number of sperm or an absence of sperm in the semen - due to prior vasectomy, trauma, varicocele, among other causes.
In this technique, our embryology team injects a single sperm directly into each egg. We monitor the development of the resulting embryos and, when indicated, perform the transfer to the uterus - with the pregnancy test scheduled 10 to 12 days later.
Frequently asked questions
The first step is to schedule a consultation with a fertility specialist. Based on the clinical evaluation and test results, it is possible to understand whether timed intercourse, intrauterine insemination, in vitro fertilization, ICSI, or another reproductive care strategy may make sense.
The information on this page is educational and does not replace an individual medical evaluation.
Schedule your consultation and understand which path may make sense for your case.
Infertility is the difficulty of becoming pregnant after a period of unsuccessful attempts. It may be related to different factors, such as changes in ovulation, the fallopian tubes, the uterus, ovarian reserve, egg quality, semen quality, reproductive age, conditions such as endometriosis, or causes that are not always identified at the beginning of the evaluation.
Infertility should not be seen as the responsibility of only one person. The evaluation needs to consider the medical history, test results, and reproductive context of the person or couple trying to conceive.
In general, an evaluation with a fertility specialist may be considered when pregnancy has not occurred after about 12 months of trying. For cisgender women and other people with ovaries who wish to carry a pregnancy and are over 35, this evaluation is usually recommended after about 6 months.
It may also make sense to seek guidance earlier when there are very irregular menstrual cycles, a history of endometriosis, pregnancy losses, abnormal semen analysis, previous surgeries, cancer treatments, use of medications that may affect fertility, or the desire to preserve eggs, sperm, or embryos for the future.
The causes can vary widely. Factors that may be involved include ovulation disorders, low ovarian reserve, advanced reproductive age, endometriosis, fallopian tube changes, fibroids or other uterine conditions, male factors, genetic conditions, a history of surgeries, cancer treatments, and unexplained infertility.
In some cases, more than one factor may be involved. That is why the evaluation should be individualized and carried out step by step, based on medical history, test results, and reproductive goals.
Yes. Difficulty becoming pregnant may be related to the woman, the man, both partners, or factors that have not yet been identified.
When the partner’s sperm will be used, tests such as a semen analysis are often part of the evaluation. Changes in sperm count, motility, morphology, or quality can affect the chances of pregnancy. In some cases, an andrology evaluation may be recommended. Andrology is the field focused on male reproductive health.
Yes. Many people with endometriosis are able to become pregnant. However, depending on the extent of the condition, symptoms, age, ovarian reserve, and other associated factors, endometriosis may affect fertility.
A medical evaluation helps determine whether it makes sense to keep trying naturally for some time, consider low-complexity treatments, or evaluate techniques such as in vitro fertilization.
No. In vitro fertilization, or IVF, is an important option within assisted reproduction, but it is not the only path.
Depending on the medical evaluation, low-complexity treatments such as timed intercourse or intrauterine insemination may be considered, as well as other reproductive care strategies. In some cases, IVF may be recommended from the beginning. In others, it may not be the first step.
The choice depends on the diagnosis, age, test results, time trying to conceive, ovarian reserve, semen quality, fallopian tube conditions, and the reproductive goals of each person or couple.
During the first consultation, we review medical history, time spent trying to conceive, previous test results, menstrual cycles, prior surgeries, previous diagnoses, family history, medication use, and reproductive goals.
When the decision involves a couple, the participation of both people is essential. Male fertility can also influence the treatment plan, so the partner’s history and test results should be considered when the couple plans to use their own sperm.
Based on this conversation, the medical team may request tests, organize the evaluation, and explain which paths may make sense.
No. The consultation can take place even if you do not have previous test results. During this appointment, the medical team reviews your history and defines which tests truly make sense for you.
If you already have tests, even older ones, they may help with the initial evaluation. Hormonal tests, ultrasounds, surgical reports, semen analysis, genetic tests, and previous medical reports may be useful when available.
The tests depend on each person’s or couple’s history and reproductive goals. In general, they may include hormonal tests, ultrasound, ovarian reserve assessment, evaluation of the uterus and fallopian tubes, infectious disease screening, general health tests, and semen analysis when the partner’s sperm will be used.
In some cases, the team may also recommend genetic evaluation, andrology assessment, or additional tests.
The definition of which tests are needed should not be generic. It must consider medical history, age, previous attempts, health background, and the treatment being evaluated.
The first step is a consultation with a fertility specialist. During this evaluation, the medical team reviews medical history, time trying to conceive, previous test results, age, menstrual cycle, ovarian reserve, uterine and fallopian tube conditions, semen evaluation when applicable, and the reproductive goals of the person or couple.
Based on this information, a low-complexity treatment such as timed intercourse or intrauterine insemination may be recommended, or a high-complexity treatment such as IVF or ICSI.
There is no single technique that is best for every case. There is the most appropriate strategy for a specific clinical situation at a specific moment.
In low-complexity treatments, fertilization takes place inside the body, with medical monitoring to identify or stimulate the most favorable time for pregnancy. These techniques include timed intercourse and intrauterine insemination.
In high-complexity treatments, fertilization takes place in the laboratory. This is the case with in vitro fertilization and intracytoplasmic sperm injection. After embryo formation and monitoring, embryo transfer may be performed into the uterus when medically indicated.
The choice between low-complexity and high-complexity treatment depends on the clinical evaluation, test results, and reproductive plan.
Timed intercourse is a low-complexity fertility treatment in which we monitor the menstrual cycle to identify the most favorable time for intercourse.
In some cases, medications may be used to stimulate or regulate ovulation. During monitoring, ultrasound exams help the medical team guide the most appropriate timing for the attempt.
This treatment is usually considered in specific situations, when spontaneous fertilization is possible and the test results suggest that this path may make sense.
Intrauterine insemination, also called IUI, is a low-complexity fertility technique. In this treatment, the cycle is monitored and, around the time of ovulation, the semen sample is prepared in the laboratory and placed directly into the uterus.
The goal is to facilitate the meeting between sperm and egg, but fertilization still takes place inside the body.
IUI may be considered in different situations, including some cases of unexplained infertility, mild semen abnormalities, use of donor sperm, or family-building plans that require donated gametes. The indication must be individualized.
In vitro fertilization, or IVF, is a high-complexity fertility treatment in which eggs are retrieved and fertilized in the laboratory with sperm from a partner or donor, depending on the case.
In general, the process may involve ovarian stimulation, ultrasound monitoring, egg retrieval, semen preparation, fertilization in the laboratory, embryo development, uterine preparation, and embryo transfer.
Not all steps happen the same way for every person. The protocol depends on the medical evaluation, test results, and the body’s response to treatment.
ICSI, or intracytoplasmic sperm injection, is a technique performed as part of in vitro fertilization. In this procedure, a single sperm cell is injected directly into the egg in the laboratory.
This technique may be considered in specific situations, such as significant semen abnormalities, low sperm count, previous fertilization history, or other factors evaluated by the medical team.
ICSI is not automatically indicated for every case. Its recommendation depends on test results, reproductive history, and the strategy defined during the consultation.
No. In intrauterine insemination, the semen sample is prepared in the laboratory and placed into the uterus during the fertile window. Fertilization takes place inside the body.
In in vitro fertilization, eggs are retrieved and fertilized in the laboratory. The embryos formed are then monitored and, when indicated, transferred to the uterus.
This difference changes the level of intervention, the treatment steps, the tests involved, and the criteria for indication.
Age influences the chances of pregnancy, response to treatment, and medical risks during pregnancy. For this reason, there is no single answer that applies to everyone.
Under the rules of the Brazilian Federal Council of Medicine, the maximum age for candidates who wish to carry a pregnancy through assisted reproduction techniques is 50. Exceptions may be evaluated based on technical and scientific criteria, considering the health of the person who wishes to carry the pregnancy and the risks involved.
During the consultation, the medical team evaluates age, medical history, test results, ovarian reserve when applicable, and pregnancy safety to guide what is possible and appropriate in each case.
Yes, it is possible, but fertility tends to decline with age, especially in people with ovaries. Some pregnancy-related risks may also increase.
A medical evaluation is important to understand realistic possibilities, clinical limits, necessary tests, and whether it is appropriate to keep trying naturally, consider assisted reproduction treatments, or evaluate alternatives such as the use of donor eggs when applicable.
When performed with medical indication and specialized monitoring, assisted reproduction treatments follow safety and monitoring protocols.
Even so, there may be risks, discomfort, and effects related to medications, procedures, ovarian response, multiple pregnancy, or the need to adjust the cycle. Before starting any step, the medical team explains the possible benefits, risks, and limits of the recommended treatment.
Some steps may cause mild discomfort, similar to routine gynecological exams. Procedures such as egg retrieval are usually performed with sedation for greater comfort.
The most important point is that each step should be explained before it happens. If there is pain, anxiety, discomfort with gynecological exams, a history of trauma, or any specific limitation, this should be discussed with the team so care can be provided with predictability, consent, and safety.
In most cases, prolonged rest is not necessary. Many people are able to maintain their routine during much of the treatment.
Some steps may require temporary adjustments, such as attending ultrasounds on specific days, having tests done, undergoing egg retrieval, or following instructions after procedures. The medical team will explain when it may be necessary to reduce activities, avoid physical effort, or reorganize the routine for a few days.
Yes. In some situations, there may be a risk of multiple pregnancy, depending on the technique used, the response to treatment, and, in IVF cases, the number of embryos transferred.
The treatment plan aims to reduce this risk whenever possible, following medical and ethical criteria. In assisted reproduction, the decision about the number of embryos must consider safety, age, embryo characteristics, and current regulations.
No. No assisted reproduction treatment can guarantee pregnancy.
These techniques may expand possibilities in certain contexts, but outcomes vary according to age, diagnosis, egg and sperm quality, uterine health, embryo development, response to medications, and other clinical factors.
That is why an important part of treatment is understanding the chances, limits, and possible next steps based on the real information from your case.
When a treatment does not result in pregnancy, the medical team reassesses the cycle, the body’s response, test results, gamete quality, embryo development when applicable, and other clinical factors.
Based on this analysis, it may be recommended to repeat the strategy, adjust medications, request new tests, change the technique, or consider other paths within assisted reproduction.
This process needs to be handled with clarity, without promising results and without treating one previous attempt as a final conclusion about all possibilities.
Yes. Before starting an assisted reproduction treatment, it is necessary to sign an Informed Consent Form, known in Brazil as the TCLE.
This document records that the person or couple received explanations about the recommended technique, the expected steps, possible risks, treatment limits, important decisions, and situations in which the plan may need to be adjusted.
The consent form is not just a formality. It is part of a conscious decision, especially in treatments that involve medications, gamete collection, laboratory fertilization, embryo transfer, freezing, donor use, or decisions about surplus embryos.
Yes. Assisted reproduction may be part of the reproductive planning of same-sex couples, transgender people, nonbinary people, people pursuing solo motherhood or fatherhood, and different family configurations.
What changes is the planning: it may be necessary to define who will provide the gametes, who will carry the pregnancy, whether donor sperm, eggs, or embryos will be used, and which documents and consents will be required.
Our care begins with an individual evaluation, technical guidance, and support so each person can understand their real possibilities, clinical limits, and next steps.
No. Any fertility treatment depends on medical evaluation, test analysis, and informed consent.
Starting medications or procedures without a consultation can increase risks, compromise the cycle, and lead to decisions that are not appropriate for your case. The consultation is the first step to understand what is happening, which tests are needed, and which strategy makes sense.
Schedule Your Consultation
Take the next step with clarity about the possibilities available to you.
Agende sua consulta